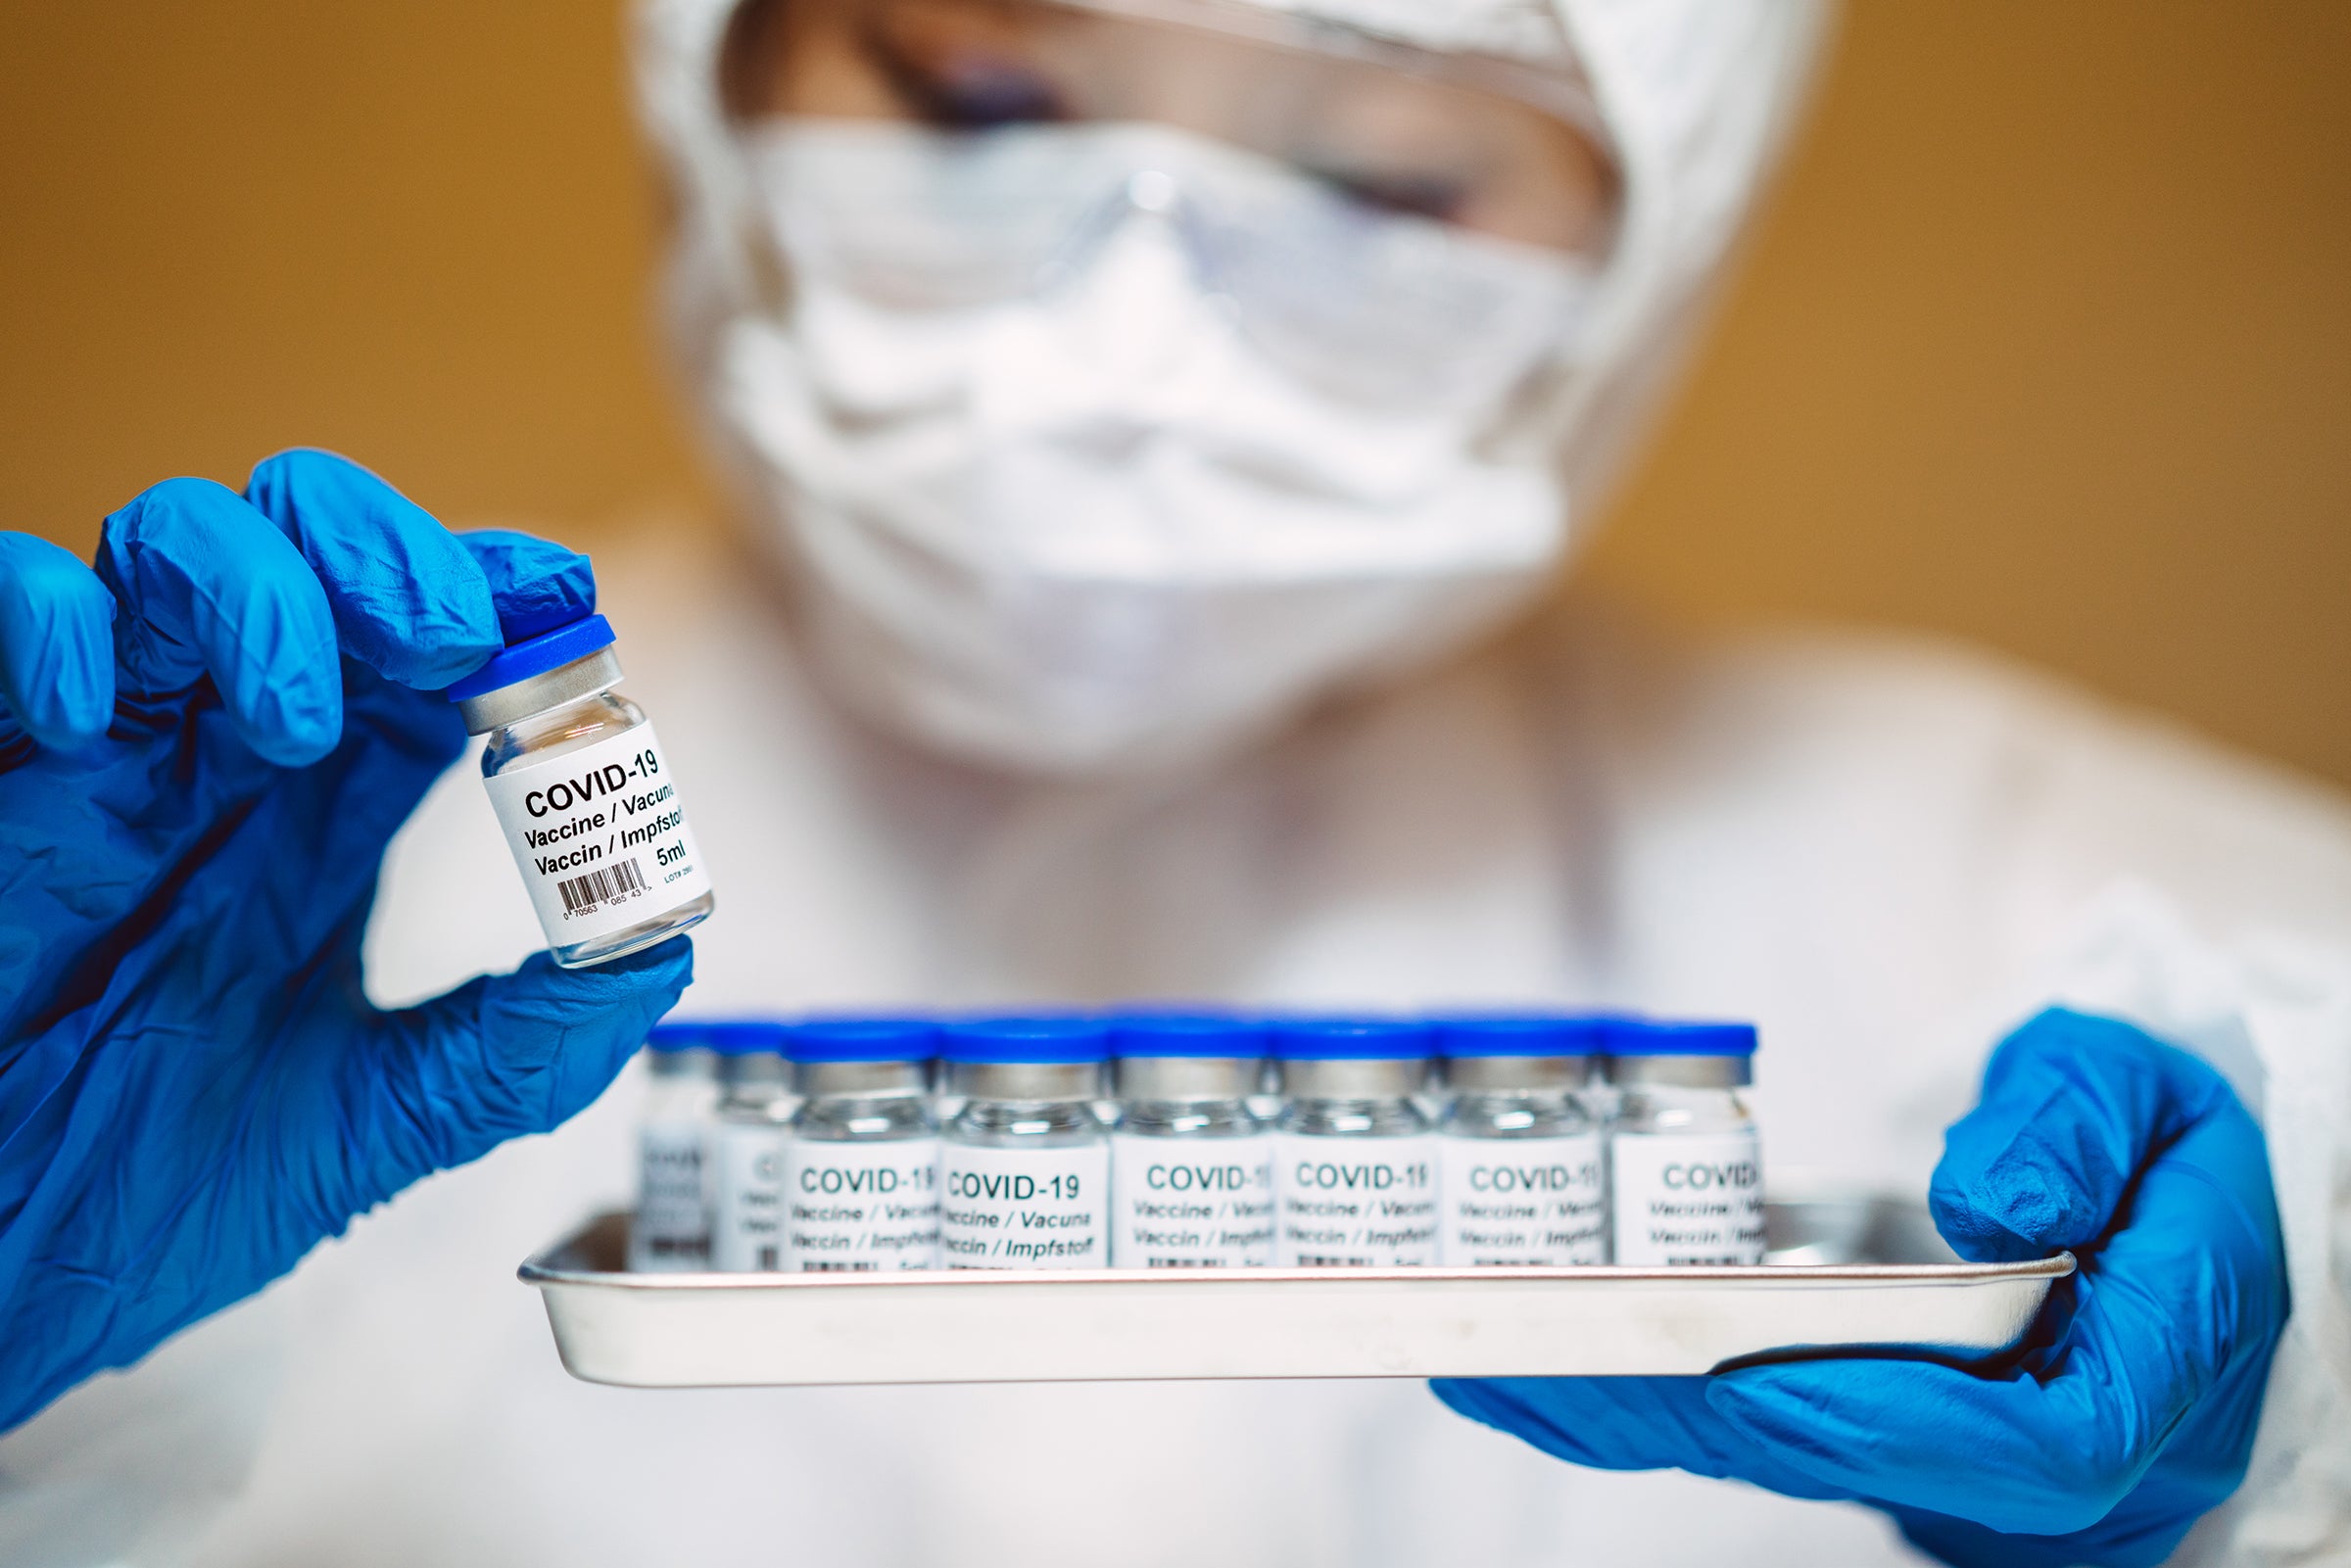
Both Pfizer and Moderna utilize the same genetically engineered vaccine method, which includes messenger RNA particles. Assuming the U.S. Fda licenses the vaccines for” emergency situation use,” each company will need to increase production and distribution tremendously. Pfizer anticipates to produce approximately50 million doses worldwide in2020 and up to 1.3 billion in2021 Moderna intends to manufacture around20 million dosages in2020 and500 million to one billion in 2021. An individual receiving either vaccine will need 2 dosages, administered three or four weeks apart.
Several steps are needed to provide a lot of little glass vials of vaccine to local health centers and pharmacies, where the medication can be injected into an individual’s arm. Moderna’s vaccine needs to be delivered at–20 degrees Celsius(– 4 degrees Fahrenheit), and it can then be stored at that temperature for 6 months. As soon as defrosted and kept in a fridge in between two and 8 degrees C (36 to46 degrees F) it benefits up to30 days. Pfizer’s vaccine must be kept at–70 degrees C(– 94degrees F)– a much greater difficulty. Once transferred to a fridge, it needs to be administered within 5 days.
.
In the U.S., Moderna will produce its vaccine in New Hampshire, Pennsylvania and Indiana. It will ship vials to McKesson Corporation’s warehouse in Irving, Tex., the center of the federal government’s Operation Lightning speed vaccination initiative. Moderna also prepares to manufacture the intervention in Switzerland and Spain. Pfizer will make its U.S. vaccine in Kalamazoo, Mich. It is not distributing through Operation Warp Speed, so it will deliver big thermal boxes of filled vials, jammed with solidified carbon dioxide, through companies such as UPS and FedEx to places around the country. Pfizer likewise has a production website in BelgiumOn November 16 the business introduced a pilot program to evaluate its delivery plan to 4 states: Rhode Island, Tennessee, Texas and New Mexico.
The system for dispersing items (including meat and chemicals) at low temperature levels is known as the “cold chain.” What will it take for this network to successfully disperse huge numbers of vials? How is vaccine securely maintained? The number of centers can even handle the obstacle, and how will that impact who gets vaccinated and when? Scientific American asked Julie Swann, a teacher and head of the department of industrial and systems engineering at North Carolina State University, to reveal the information. Swann specializes in health care supply chains, and she was on loan to the U.S. Centers for Illness Control and Prevention throughout the emergency response to the 2009 H1N1 swine influenza pandemic.
[An edited transcript of the interview follows.]
Moderna’s shipping temperature will be–20 degrees C. Is that typical for frozen items? And is Pfizer’s temperature of–70 degrees C extreme?
There are different cold chains. The ultralow chain, the deep freeze, is the one at–70 degrees C. There’s the “frozen” chain, at–20 degrees C, which is more like a routine freezer. And then [there is] the cooled chain: Many vaccines, like influenza vaccines, are refrigerated between two and eight degrees C. Only a couple have to be adhered–20 C, such as [those for] varicella and zoster. The Ebola vaccine did have an ultracold supply chain. Some animal vaccines, like vaccines for chickens, are kept ultracold, too.
What type of centers can deal with–70 degrees C?
Not that numerous. They could possibly send out vaccines from there to their retail stores, all of which will have preplanned who is going to get immunized.
The vaccines do not need to remain frozen right up to the time of shot.
The CDC has a playbook for states, openly readily available, that sets out what you can do with vaccine type A or vaccine type B. It states as soon as a center receives a thermal shipper [such as that from Pfizer], it needs to replace the solidified carbon dioxide within 24 hours and once again every five days. And you can just open the box one or two times a day. After day 15 from when the vials were produced, they need to be transferred to refrigerated temperatures and used within 5 days. There is some time to vaccinate people.
Pfizer’s thermal carrier holds 975 vials.
I don’t see that as a challenge in the U.S. Cargo business require to make cash right now, so they’ll run extra flights if they need to get the 50 million doses to the locations. They desire to cut the additional 2 days off the lead time: Moderna vaccine initially goes to the McKesson distribution center and, from there, goes to the companies– that probably includes a couple of days. Worldwide, nevertheless, the difficulty of a Pfizer vaccine is rather significant.
Each Pfizer vial in fact provides five dosages. How is that handled?
The place doing immunization adds a dilutant, producing five doses. At that point the solution benefits 6 hours. A center has to figure out how lots of health care employees or customers will be immunized, and it begins the dilution procedure for that day.
It seems like places need to line up a great deal of receivers so vaccine is not wasted.
What I have actually seen is that each Pfizer tray has 195 vials, each with 5 doses, so that has to do with 1,000 dosages. And a box can hold up to 5 trays. If, in the beginning, you are prioritizing by immunizing just frontline employees who are handling COVID-19 patients, you ‘d want to line up sufficient individuals at one location to use a tray of vaccines within 5 days, or have people from the region concerned you. States might also purchase sub-80 freezers. The New york city State plan states it will set up a number of local warehouse. If they do that, then they will probably have sub-80 freezers at each place. I don’t understand if their strategy will alter now that Moderna has brought out more details.
I believe most states will not have the resources to set up local distribution. What I would do if I were them is try to find large medical facilities that do have the freezers and utilize those as the points of circulation. I would definitely partner with the local pharmacies. And I would look at models where you drive some of it around: deliver it to one location, then drive a regional van around with refrigeration that can store vials for 5 days. And you can ask individuals to drive to locations to get immunized. I think all of these [steps] will take place. Of course, there will be concerns of equity, a minimum of in the start, when vaccination depends on just the Pfizer vaccine.
What about putridity? Pharmaceutical companies report that from 5 to 20 percent of other vaccines spoil during circulation.
That will have be factored in. There is a method to keep track of the thermal carrier with a temperature level probe. In the perfect world, the monitoring would decrease to the individual vial, however I don’t understand if existing innovation will allow that. We might look at how Ebola vaccine has been distributed around Africa; it is a customized cold chain.
What about production quality assurance?
In typical vaccine production and shipping, effectiveness and stability are examined. Pfizer and Moderna are doing that.
All of this is made complex by the truth that everyone needs to get 2 injections, three or four weeks apart. Immediately, the number of people who could be immunized is cut in half.
And for each individual, your second dosage has to be the very same as your first dose, either Pfizer or Moderna.
We’ll all need accurate records.
There are a lot of obstacles with the details side of the supply chain. The companies are sending out product to suppliers, but they are not responsible for who gets immunized.
That’s mostly how public health works. There’s one system for buying and shipping vaccines, but it does not inform you anything after a vaccine has come to a place. Normally, each state uses its own system for registering who receives vaccine– that’s called the immunization pc registry. Those 2 systems don’t talk to each other, so without the addition of another layer, it’s difficult for states to understand this place has 50 doses left, this area is entirely out– that sort of details. The federal government did purchase a system that would enable such ability, but states might be utilizing their own.
There are systems that can do this– like those that coordinate diagnostic testing. They offer two real benefits: One is that you can inform consumers where they can go to get [a] vaccine– not where it’s been delivered but if there’s any. Or localities can increase public messaging to raise need for a vaccine, because we understand there will be issues with people being hesitant to get it.
I picture the vaccination prioritization schedules that we’re simply hearing about could make info tracking even harder– you know, frontline workers ought to get the vaccines initially, then teachers, and so on.
The National Academy of Medication suggests phases: first high-risk employees in health care facilities plus first responders, then individuals with underlying conditions that put them at high threat, then, later, instructors, then young adults, then the rest of us. There is also talk about sending the early vaccines to areas of high frequency of illness.
Due to the fact that it’s likely that only big institutions might provide ultracold storage, it has been recommended that Pfizer’s vaccine might wind up going to cities and Moderna’s vaccine could end up going to less densely inhabited locations. However these are commercial business. Why would they limit their markets?
When we have enough supply of any vaccine you want, then the market will choose Moderna over Pfizer– as long as the security and efficacy are high enough– since of the refrigeration distinction. In the early phases, with so lots of people all over needing vaccine, I believe a lot of decisions will be made based on what is finest for the system.
Learn More about the coronavirus break out from Scientific American here And read coverage from our worldwide network of publications here

Comments
Post a Comment